Twenty Minutes With a Medical Assistant: The Most Underrated Part of Your Doctor's Appointment
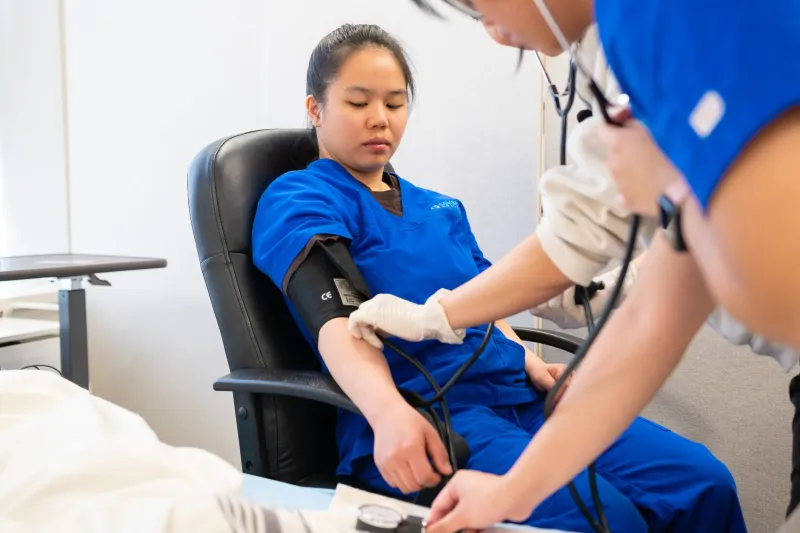
Most patients treat the first stretch of a doctor's appointment as a formality — a speed bump between the waiting room and the real conversation. A cuff squeezes your arm, a thermometer beeps, someone types while asking about your medications. Then the doctor walks in and the visit "really" begins.
That assumption costs you. The intake period, typically handled by a medical assistant (MA), is where the raw data of your visit is collected — and where your physician's attention gets directed. Used well, those twenty minutes can sharpen your diagnosis, surface concerns you might otherwise forget, and make the ten minutes you get with the doctor dramatically more productive.
What's Actually Happening in Those Twenty Minutes
A medical assistant's pre-visit routine is more layered than it looks. In a typical internal medicine or family practice visit, the MA will:
- Verify your identity and medications. This is a safety check, not paperwork theater. Medication reconciliation catches dangerous interactions, duplications, and expired prescriptions.
- Record vital signs. Blood pressure, heart rate, temperature, respiratory rate, and often oxygen saturation and weight. These numbers become the baseline your doctor interprets everything else against.
- Update your history. Allergies, family history changes, new diagnoses from specialists, recent hospitalizations.
- Ask your reason for the visit. Often verbatim, sometimes with follow-up questions about timing, severity, and what you've already tried.
- Flag screenings and preventive care. Many practices prompt MAs to confirm whether you're due for a mammogram, colonoscopy screening, A1c test, or vaccinations.
- Prepare the chart. The MA summarizes all of this so your doctor walks in already oriented.
That last point matters most: your physician's first impression of your visit is often the MA's note. A vague intake — "stomach hurts" — produces a vague visit.
Why They Ask Questions Your Doctor Will Ask Again
Patients frequently get frustrated: "I just told the other person this." The repetition is intentional, and it serves two purposes.
First, consistency checks. If your story shifts between the MA and the physician, it's usually not a problem — people remember details under follow-up probing. But inconsistencies can also flag confusion, memory issues, or distress worth exploring. Clinicians are trained to notice the pattern, not to police it.
Second, triage of attention. Your doctor has maybe fifteen minutes. The intake answers help them decide what to prioritize. A medication change buried in the MA's notes might get a full discussion; something you only mention at the end of the visit might get rushed.
What to Say — and How to Say It
Lead with specifics, not adjectives. "Dizzy when I stand up, twice a week, for about a month" gives your care team far more than "I've been dizzy." Timing, frequency, and triggers are the vocabulary of diagnosis.
Bring a written list. Top three concerns, in order. Hand it over or read from it during intake. MAs will often type your list directly into the chart, guaranteeing your doctor sees it.
Report numbers honestly. If your home blood pressure readings run 140/90 but the office reading is 122/78, say so — and bring the log. White coat hypertension is real, and home readings genuinely change treatment decisions.
Disclose the supplements. Roughly a third of patients don't mention vitamins, herbal products, or over-the-counter sleep aids because they don't consider them "medications." Some — St. John's wort, high-dose fish oil, ginkgo — interact with prescriptions. The MA's medication list is only as safe as what you put on it.
Be candid about adherence. If you stopped taking a medication because of cost or side effects, say that plainly. Doctors can't adjust a plan they think you're following.
What Not to Do
- Don't save the big reveal for the end. Chest pain, suicidal thoughts, or new neurological symptoms should be stated at intake, not as you're standing up to leave. MAs are trained to escalate urgent complaints immediately.
- Don't downplay to seem stoic. Rating your pain a 3 when it's a 7 doesn't make you a good patient; it starves your doctor of information.
- Don't hand over a phone with 40 photos of rash. Pick the two or three most representative and tell the story chronologically.
Your Vital Signs Are a Conversation, Not a Verdict
Two numbers deserve your attention during intake. Blood pressure taken too quickly after you sit down — before the recommended five minutes of rest — often reads artificially high. If your first reading seems off, it's entirely reasonable to ask for it to be retaken after a few minutes of quiet sitting, on both arms if the values differ.
Weight, too, is data, not judgment. Sudden, unexplained changes in either direction are clinically meaningful, so report them accurately even when it's uncomfortable.
A Simple Pre-Visit Checklist
The night before your appointment, jot down:
- Your top three concerns, ranked.
- All medications, supplements, and doses (or photograph the bottles).
- Any home readings — blood pressure, glucose, weight trends.
- Changes since your last visit: new symptoms, new doctors, new prescriptions, life stressors.
This five-minute habit transforms the intake from an interrogation into a briefing. The medical assistant gets accurate data, the chart gets organized, and your physician walks in ready to solve problems instead of reconstructing history.
The invisible twenty minutes of your appointment isn't a waiting room with a blood pressure cuff. It's the foundation of your care — and it's the part of the visit you have the most control over.


